
Tele-intensive Care Unit Market Report Scope & Overview:
The global Tele-intensive Care Unit market size was valued at USD 4.64 billion in 2025 and forecast to reach USD 5.32 billion by 2026, growing at a compound annual growth rate of 14.67%. The tele-ICU market is expected to grow from USD 5.32 billion in 2026 to USD 18.24 billion by 2035, at a CAGR of 14.67%. This growth is being driven by an increasing demand for staffing intensive care units with limited available critical care specialists throughout a number of beds/sites in hospitals.
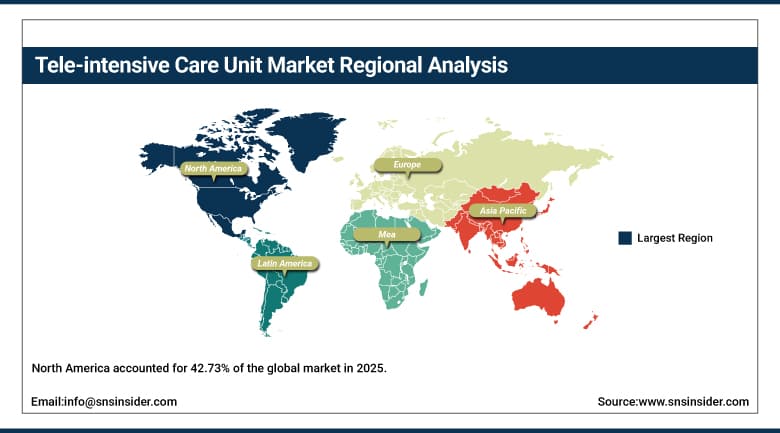
In terms of geography, North America dominates the market with the largest share of 42.73% in 2025 owing to the high adoption rate of remote critical care delivery, reimbursement mechanisms, and presence of large hospital chains operating command centers. Europe is in the second place due to the presence of the national health service systems and private hospital systems providing remote services to regional hospitals. APAC region is expected to be the fastest growing region due to the presence of India, China and Japan and addition of beds to the intensive care units through the use of remote specialists to provide services in districts having few physicians.
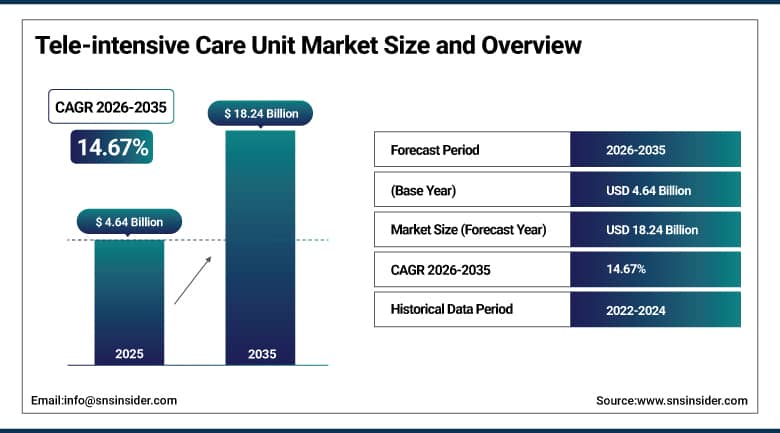
To Get More Information On Tele-intensive Care Unit Market - Request Free Sample Report
Key Report Takeaways
- By component, hardware held a 61.84% share in 2025, while software is the fastest growing.
- By type of management, open with consultant models accounted for a 34.86% share in 2025, while the intensivist model is the fastest growing.
- By delivery model, centralized programs represented a 49.83% share in 2025, while hybrid models are the fastest growing.
- By end user, hospitals commanded a 32.47% share in 2025, while homecare settings are the fastest growing.
- By region, North America led with a 42.73% share in 2025, while Asia Pacific is the fastest growing.
Market Trends and Insights
Predictive alerts are moving from pilot to standard practice. Algorithms that scan vital signs, laboratory values, and nursing notes flag early deterioration, so remote intensivists can intervene hours before a crisis, and hospitals now ask vendors to demonstrate alert quality before contracting.
Hub-and-spoke designs are spreading beyond single health systems. Regional and state hubs now serve dozens of smaller hospitals from one command center, and several programs mix remote specialists with on-site teams rather than replace them.
Virtual nursing and camera-based observation are widening the scope of tele-ICU platforms. The same infrastructure that supports intensivist rounds is being used for sitters, discharge education, and step-down units, which raises utilization of installed equipment.
Drivers Impact Analysis
|
Driver |
(~) Percentage Point Impact on Market CAGR |
Geographic Relevance |
Impact Timeline |
|---|---|---|---|
|
Intensivist Shortage and Rising ICU Workload |
+5.74% |
Global, strongest in rural United States and India |
Short term (2 years or less) |
|
Aging Populations and Chronic Disease Burden |
+4.38% |
North America, Europe, and Asia Pacific |
Medium term (2 to 4 years) |
|
Reimbursement and Telehealth Policy Support |
+3.62% |
North America |
Short term (2 years or less) |
|
Remote Monitoring and AI Analytics Integration |
+2.81% |
North America and Asia Pacific |
Medium term (2 to 4 years) |
|
Public Sector Critical Care Programs |
+2.07% |
North America and Asia Pacific |
Long term (4 years or more) |
Intensivist Shortage and Rising ICU Workload
Few hospitals can place a board-certified intensivist at every bedside around the clock, and the gap is widest in rural and small community facilities. Remote programs let one specialist oversee many units, extending expert supervision to sites that could not recruit locally. For example, workforce data from the Association of American Medical Colleges show that the United States had 14,159 critical care physicians in 2022, a small number against the volume of intensive care beds. Tele-ICU therefore functions as a practical means of spreading scarce expertise across many hospitals.
Aging Populations and Chronic Disease Burden
Older patients with heart failure, respiratory disease, and sepsis account for a large share of intensive care admissions, and their numbers are rising in North America, Europe, Japan, and China. Hospitals with limited capacity need ways to monitor sicker patients safely without transferring them. The United States operates 112,369 intensive care beds, according to American Hospital Association data compiled by the Society of Critical Care Medicine, and each of those beds is a potential point of remote coverage. Longer stays and more complex cases raise the value of continuous oversight.
Reimbursement and Telehealth Policy Support
Payment rules shape adoption strongly, because hospitals commit capital only when remote services can be billed or financed. In the United States, the Department of Health and Human Services reported in February 2026 that recent legislation extended many Medicare telehealth flexibilities through the end of 2027, which gives health systems a longer planning horizon. Similar support appears in national digital health strategies elsewhere. Certainty on payment lowers the risk of building command centers and encourages hospitals to expand coverage from a single unit to entire networks of facilities.
Remote Monitoring and AI Analytics Integration
Continuous streams from bedside monitors, ventilators, and infusion pumps can now be combined with electronic record data in a single view. Software scores deterioration risk, prioritizes patients for review, and documents interventions, so each remote clinician can supervise more beds without loss of quality. Cloud deployment reduces the need for local servers, which shortens installation time at small hospitals. Vendors that integrate directly with major record systems also lower the burden on hospital information technology teams, a point that increasingly decides procurement and strengthens the clinical and economic case.
Public Sector Critical Care Programs
Government health systems are sponsoring tele-ICU networks to extend specialist care to dispersed populations. In July 2026 the U.S. Department of Veterans Affairs activated TeleCritical Care at the Malcom Randall Medical Center in Gainesville, Florida, adding to its national network of affiliated sites. State programs in India are following hub-and-spoke designs that link district hospitals to government-run command centers. Because public buyers usually contract for multiple years and many sites, such programs create stable demand for hardware, software, and clinical staffing services.
Restraints Impact Analysis
|
Restraint |
(~) Percentage Point Impact on Market CAGR |
Geographic Relevance |
Impact Timeline |
|---|---|---|---|
|
High Setup and Operating Cost |
-1.62% |
Global, strongest in small hospitals |
Medium term (2 to 4 years) |
|
Interoperability Gaps with EHR Systems |
-1.18% |
Global |
Medium term (2 to 4 years) |
|
Data Privacy and Cybersecurity Concerns |
-0.74% |
Global |
Long term (4 years or more) |
|
Variable Reimbursement and Clinician Acceptance |
-0.41% |
North America and Europe |
Long term (4 years or more) |
High Setup and Operating Cost
A tele-ICU installation requires cameras, monitoring interfaces, secure networks, and a staffed command center, and the combined cost can be difficult for small hospitals to justify. Ongoing fees for clinician coverage, software licenses, and maintenance add to the burden. Benefits such as shorter stays and fewer transfers appear over time rather than immediately, which complicates budgeting for institutions with thin margins. Smaller facilities therefore tend to join shared programs operated by larger systems, and adoption in independent hospitals remains slower than the clinical case alone would suggest.
Interoperability Gaps with EHR Systems
Remote intensivists need accurate, real-time access to medication lists, laboratory results, and device data, yet hospitals use many different record systems and monitoring brands. Interfaces must often be built and tested for each site, which delays go-live dates and increases cost. Inconsistent data formats can also produce gaps in remote views, reducing clinician trust in the platform. Progress on common standards is steady, but integration remains a major technical hurdle, especially in older facilities and in emerging economies with fragmented health information infrastructure.
Data Privacy and Cybersecurity Concerns
Streaming patient video and physiological data across networks introduces exposure to interception and intrusion. Hospitals must secure endpoints, authenticate remote clinicians, and comply with privacy laws that differ by country and, in some cases, by state. A single incident can disrupt critical care operations and damage public trust, so boards demand strong safeguards before approving programs. Meeting these requirements raises costs and lengthens procurement, and concerns are most acute where hospitals lack dedicated security staff or where rules on cross-border data transfer remain unsettled.
Variable Reimbursement and Clinician Acceptance
Payment for remote critical care still varies by payer, region, and care setting, and some hospitals hesitate to invest where coverage may change. Clinician attitudes also matter, since bedside nurses and local physicians may perceive remote oversight as intrusive or as a challenge to their judgment. Successful programs address this through clear role definitions, training, and gradual rollout, but change management takes time. In smaller hospitals with limited staff, these human factors can slow adoption even after technical and financial barriers have been resolved.
Tele-intensive Care Unit Market Segment Analysis
By Component, Hardware Dominates Tele-intensive Care Unit Market; Software to Register Fastest Growth.
Hardware forms the largest block of spending because every tele-ICU site needs cameras, display panels, bedside monitoring interfaces, communication lines, and workstations before any service can begin. Initial deployments are capital intensive, and hospitals commonly purchase equipment for every bed in a connected unit. Physiological monitors and therapeutic devices that feed data to remote clinicians add further outlays, while upgrade cycles keep replacement demand steady. Hardware accounted for 61.84% of the market in 2025, well ahead of software and services.
Software is growing fastest because hospitals want predictive scoring, workflow tools, and record integration that continue to improve after installation. Subscription pricing lowers entry barriers for smaller hospitals, and cloud delivery allows vendors to update algorithms without site visits. As more installations are completed, buyers shift attention from equipment to analytics that raise the productivity of each remote clinician, and this shift supports a CAGR of 16.77% from 2026 to 2035, well above the market as a whole.
By Type of Management, Open with Consultant Models Dominate Tele-intensive Care Unit Market; Intensivist Model to Register Fastest Growth.
Open with consultant arrangements lead since they preserve the authority of local attending physicians while giving them access to remote intensivists for advice when needed. Hospitals find this structure easier to introduce, as it fits existing medical staff bylaws and avoids disputes over who directs patient care. Costs are also lower than those of full remote management, which suits community hospitals with modest budgets. This model represented 34.86% of the market in 2025, ahead of every other structure.
The intensivist model is growing fastest because outcomes data from closed arrangements have encouraged health systems to place remote specialists in direct charge of order entry and escalation. Hospitals that struggle with after-hours coverage find that dedicated remote teams provide consistent protocols and faster response to alarms. Smaller hospitals also appreciate clear escalation pathways and order sets. Rising shortages of local critical care physicians push more facilities toward this approach, supporting a CAGR of 16.57% from 2026 to 2035 worldwide.
By Delivery Model, Centralized Programs Dominate Tele-intensive Care Unit Market; Hybrid Models to Register Fastest Growth.
Centralized command centers remain the most common design because one hub can monitor many hospitals using shared staff, standard protocols, and a single technology stack. Health systems that already operate multiple facilities can reuse existing infrastructure, which lowers the cost per covered bed. Central teams also build experience with a wide range of cases, improving consistency of care across sites. Shared analytics and reporting tools also simplify quality review for administrators. Centralized programs held 49.83% of the market in 2025.
Hybrid designs are expanding fastest as hospitals combine a central hub with local clinicians and distributed specialists who can join at different hours. This flexibility suits regions with uneven connectivity and mixed levels of staffing. Hospitals also value being able to scale coverage by unit or by shift, rather than committing to a complete model at the start. Pilot phases can be funded within existing departmental budgets. These benefits support a CAGR of 15.10% from 2026 to 2035.
By End User, Hospitals Dominate Tele-intensive Care Unit Market; Homecare Settings to Register Fastest Growth.
Hospitals lead because intensive care is delivered mainly inside acute care facilities, and these institutions carry the staffing pressure that tele-ICU is meant to ease. Large systems build their own command centers, while community hospitals subscribe to programs run by regional partners. Purchasing decisions are made at the institutional level, with budgets that cover equipment, software, and clinical services. Multiyear service contracts with remote providers keep these buyers engaged. Hospitals accounted for 32.47% of the market in 2025.
Homecare settings are growing fastest as step-down and chronic respiratory patients are cared for outside hospitals under remote supervision. Wearable monitors and secure video links allow specialists to follow patients after discharge and identify deterioration early, which reduces readmissions. Caregivers also gain reassurance from continuous specialist visibility. Health plans and hospital-at-home programs are supporting these arrangements, since they can lower the cost of long stays, and this momentum supports a CAGR of 17.12% from 2026 to 2035 worldwide.
Geography Analysis
|
Region |
Major Country |
Share within Region, 2025 (%) |
|---|---|---|
|
North America |
United States |
86.14% |
|
Europe |
Germany |
27.68% |
|
Asia Pacific |
China |
41.37% |
|
Middle East & Africa |
Saudi Arabia |
33.86% |
|
Latin America |
Brazil |
48.29% |
North America Tele-intensive Care Unit Market
North America accounted for 42.73% of the global market in 2025. Hospitals in the region adopted remote critical care earlier than most peers, and large health systems now run command centers that cover dozens of facilities. Established payment pathways, strong broadband coverage, and a deep base of intensivists employed by remote programs support the position. Rural hospitals, which struggle to staff intensive care units, remain a key source of demand for subscription-based coverage models that reduce the need for patient transfers.
The United States contributed USD 1.71 Billion in 2025 and is forecast to grow at a CAGR of 15.06% from 2026 to 2035. Federal health programs, including those operated for veterans, continue to extend remote critical care to additional sites, and private systems are consolidating regional hubs. Canada adds activity through provincial programs that connect northern and remote hospitals to urban centers, where specialists can review cases through shared video and data links, often at any hour of the day or night.
Get Customized Report as Per Your Business Requirement - Enquiry Now
Europe Tele-intensive Care Unit Market
Europe is the second-largest region, shaped by national health services and private hospital groups that are extending remote oversight to smaller regional hospitals. Germany, the United Kingdom, and France lead activity, while Nordic countries use remote links to cover sparse populations across long distances. Hospitals in the region often pair tele-ICU with existing electronic record platforms, and procurement frameworks tend to favor vendors that meet strict data protection requirements. Several national programs also fund pilot projects that test remote coverage in district hospitals.
Staffing remains a pressing issue, as several countries report vacancies among intensive care nurses and physicians. Remote support helps hospitals maintain coverage during nights and weekends without closing beds, and some health systems use shared platforms to train junior staff. Cross-border collaboration on digital health standards is improving compatibility, although procurement cycles remain long and are often tied to public budgets that are reviewed once a year. Hospitals that serve large rural catchment areas see particular value in this arrangement today.
Asia Pacific Tele-intensive Care Unit Market
Asia Pacific is the fastest-growing region, expected to expand at a CAGR of 16.81% from 2026 to 2035. India leads activity through private hospital networks and state programs that link district hospitals to specialist command centers. For instance, the Karnataka health department announced in November 2024 a phased rollout that connects 41 taluk hospitals to four government hubs. China and Japan add demand from large hospital systems that are expanding intensive care capacity and building regional referral networks around them.
A shortage of trained intensivists outside major cities is the main force behind adoption, and remote links allow a small specialist workforce to supervise many more beds. Local technology firms are offering lower-cost platforms, including artificial intelligence supported monitoring, which lowers entry barriers for district hospitals. Government digital health missions in several countries are also encouraging hospitals to adopt interoperable platforms. Australia and South Korea contribute mature programs that serve remote regions, while Southeast Asian countries are beginning pilots in leading public hospitals.
Latin America Tele-intensive Care Unit Market
Latin America is led by Brazil, where large private hospital networks and public university hospitals are building remote critical care programs. Mexico, Argentina, and Colombia follow, with activity concentrated in major cities and in the networks of private insurers. Demand arises from intensive care units that lack sufficient specialists outside metropolitan areas, and remote coverage lets hospitals manage complex patients locally rather than transferring them over long distances. Tertiary hospitals in large cities can act as hubs for smaller institutions in surrounding regions.
Economic volatility and uneven connectivity restrain the pace of adoption, so many programs begin with a single hospital group or a regional partnership. Local vendors and telecom operators are supplying connectivity and monitoring packages tailored to smaller budgets. Public and private partnerships are emerging in several countries, and as broadband coverage improves and payers recognize savings from fewer transfers, the region should see steady growth in covered beds. Training programs for local nurses and technicians are increasingly bundled into vendor contracts.
Middle East & Africa Tele-intensive Care Unit Market
Middle East & Africa is the smallest region, but investments in new hospitals in Saudi Arabia and the United Arab Emirates are creating opportunities for integrated command centers. Gulf health systems favor remote critical care to extend expertise from flagship hospitals to regional facilities, and government digital health strategies encourage such projects. Operators from Europe and India often partner with local hospital groups to supply technology and clinical coverage, which speeds up launch times and reduces the burden on local staff.
In Africa, South Africa and Kenya lead early adoption, though limited intensive care capacity and workforce shortages restrict scale. Donor-supported projects and mobile network operators are building connectivity for district hospitals, and remote consultation is used to guide care in units with few specialists. Wider adoption depends on reliable power, broadband, and training, yet the shortage of critical care physicians makes remote support an attractive option over the long term. Clear telehealth regulations in each country will be needed to support such services.
Competitive Landscape
The market is moderately concentrated. A small group of specialist remote-care providers, one large medical technology company, and a set of regional programs operated by health systems account for most covered beds. Competition revolves around clinical outcomes, depth of intensivist staffing, technology integration, and contract flexibility. Hospitals frequently compare managed-service models, in which the vendor supplies clinicians, against software-only offerings that rely on their own staff, and this choice shapes pricing.
Vendors pursue acquisitions, product launches, and partnerships to expand coverage. Consolidation among virtual care providers is combining intensivist networks with virtual nursing and telemetry services under one contract. Product work centers on predictive alerts, camera-based observation, and tighter links with record systems. Partnerships with community hospitals, technology firms, and public programs extend geographic reach, particularly in India and the rural United States.
Tele-intensive Care Unit Market Industry Leaders
1. Hicuity Health (formerly Advanced ICU Care): Intensivist-led tele-ICU provider that also offers virtual nursing, telemetry monitoring, and shared clinical services.
2. Philips: Operator of the eICU program, which combines audio-video links, predictive analytics, and 24/7 remote clinician monitoring for hospitals.
3. Cloudphysician: Indian provider of artificial intelligence supported tele-ICU services delivered through its RADAR platform and command centers.
4. Avel eCare: U.S. telemedicine company offering 24/7 critical care and ICU monitoring services backed by board-certified intensivists.
5. Equum Medical: U.S. provider of tele-critical care that gives hospitals 24/7 consultative coverage for high-acuity patients.
Companies Covered in this Report
- Hicuity Health
- Philips
- Cloudphysician
- Avel eCare
- Equum Medical
- Access TeleCare
- Caregility
Recent Industry Developments
- August 2026: DocGo signed a definitive agreement to acquire Hicuity Health, a provider of tele-ICU, virtual nursing, and telemetry services.
- August 2025: Equum Medical began 24/7 tele-ICU coverage at Starr Regional Medical Center on a virtual care platform developed with a technology partner.
- November 2024: Cloudphysician raised a Series A funding round led by Peak XV Partners to expand its artificial intelligence supported critical care services.
- August 2024: Aster DM Healthcare launched a tele-ICU service under Aster Connected Care, with a 24/7 command center and plans for hub-and-spoke expansion.
- July 2024: UAB Medicine opened its first expanded tele-ICU hospital at Whitfield Regional Hospital, where remote intensivists monitor an eight-bed unit.
- June 2024: Masimo partnered with Cleveland Clinic on hospital-based remote patient monitoring that includes TeleCritical Care.
Scope and Research Methodology
This report defines the Tele-intensive Care Unit Market as the commercial value of remote critical care programs in which off-site intensivists, nurses, and decision-support software supervise patients in hospital intensive care units through audio-video links and monitoring data. It covers hardware, software, and related services sold to hospitals, specialty centers, ambulatory surgical centers, and homecare programs. The base year is 2025, the forecast period runs from 2026 to 2035, and all values are expressed in USD. Segmentation covers component, type of management, delivery model, end user, and region, with leading countries analyzed within each region.
Secondary research forms the first layer of work and draws on company annual reports, investor presentations and filings, regulator and government databases, trade association data, product documentation, and peer-reviewed and industry publications. Primary research follows, through structured interviews and surveys with executives, product and business heads, procurement managers, and end-user stakeholders across the value chain. Responses are used to validate assumptions, adoption rates, and pricing, and to test how hospital demand is likely to change by region and care setting. Findings from both routes are cross-referenced before use. Analysts also review company disclosures for installed-base and contract information.
Market engineering begins with a bottom-up build from vendor revenue and installed capacity data, which is then cross-checked top-down against end-user spending and sector indicators such as intensive care bed counts. Triangulation continues until the two routes converge. The forecast reflects adoption trends, regulation, technology change, and macroeconomic conditions, and sensitivity checks test the stability of key assumptions. Senior analysts review every estimate and narrative section for accuracy and consistency before the final model is released. Regional estimates are checked against national health expenditure patterns, hospital counts, and intensive care capacity so that country totals align with the global figure. Forecast scenarios are then stress tested against slower adoption and delayed reimbursement.
Tele-intensive Care Unit Market Report Scope:
| Report Attributes | Details |
|---|---|
| Market Size in 2025 | USD 4.64 Billion |
| Market Size by 2035 | USD 18.24 Billion |
| CAGR | CAGR of 14.67% From 2026 to 2035 |
| Base Year | 2025 |
| Forecast Period | 2026-2035 |
| Historical Data | 2022-2024 |
| Report Scope & Coverage | Market Size, Segments Analysis, Competitive Landscape, Regional Analysis, DROC & SWOT Analysis, Forecast Outlook |
| Key Segments | • By Component (Hardware, Software, and Services) • By Type of Management (Open with Consultant, Intensivist, Co-managed, and Open) • By Delivery Model (Centralized, Decentralized, and Hybrid) • By End User (Hospitals, Specialty Centers, Ambulatory Surgical Centers, and Homecare Settings) |
| Regional Analysis/Coverage | North America (US, Canada), Europe (Germany, UK, France, Italy, Spain, Russia, Poland, Rest of Europe), Asia Pacific (China, India, Japan, South Korea, Australia, ASEAN Countries, Rest of Asia Pacific), Middle East & Africa (UAE, Saudi Arabia, Qatar, South Africa, Rest of Middle East & Africa), Latin America (Brazil, Argentina, Mexico, Colombia, Rest of Latin America). |
| Company Profiles | Hicuity Health, Philips, Cloudphysician, Avel eCare, Equum Medical, Access TeleCare, Caregility |

Frequently Asked Questions
The market was valued at USD 4.64 Billion in 2025 and is estimated at USD 5.32 Billion in 2026. It is forecast to reach USD 18.24 Billion by 2035.
The market is projected to expand at a CAGR of 14.67% from 2026 to 2035.
North America led with a 42.73% share in 2025. Asia Pacific is the fastest-growing region, with a CAGR of 16.81% from 2026 to 2035.
Hardware, open with consultant models, centralized programs, and hospitals lead their axes. Software, the intensivist model, hybrid models, and homecare settings grow fastest.
Hicuity Health, Philips, Cloudphysician, Avel eCare, and Equum Medical are the best-documented providers.
